Vision problem
Laser Presbyopia Correction in Paris
From age 40, vision changes. An emmetropic person who has seen perfectly all their life discovers they have to hold their phone farther away to read and need more light. A farsighted person, already struggling up close, notices that their distance vision is blurring too. A nearsighted person, for their part, discovers they have to take off their glasses to read. And that without them, they actually see quite well up close.

Dr Steven Nahaisi
Updated on 15 October 2026 · 28 min read
This is presbyopia. It affects everyone, without exception. With it come reading glasses, then progressive lenses, sometimes several pairs depending on needs: one on your nose, one in your bag, one on your desk.
Laser surgery can considerably reduce this dependence, at distance as well as up close. The goal is to make you independent for the vast majority of everyday tasks: reading your messages, working on a screen, driving, shopping, cooking, all without glasses.
But presbyopia is probably the most complex subject in refractive surgery, because it relies entirely on acompromise between distance vision and near vision. This compromise must be understood and accepted before having surgery. My role is to find the balance that suits you, the one that will change your daily life.
Here I explain how presbyopia works, which strategies exist depending on your profile, what to expect from surgery, and the real questions my patients ask me every week.
On this page12 sections
- 02UNDERSTANDING PRESBYOPIA
- 03CORRECTION STRATEGIES DEPENDING ON YOUR PROFILE
- 04THE TECHNIQUES: BLENDED VISION, PRESBYMAX AND PRESBYLASIK
- 05THE DISTANCE/NEAR COMPROMISE AND HALOS
- 06TRANSPRK FOR PRESBYOPIA
- 07BEFORE SURGERY
- 08THE SURGERY AND RECOVERY
- 09RESULTS AND REALISTIC EXPECTATIONS
- 10REVERSIBILITY AND ENHANCEMENTS
- 11FREQUENTLY ASKED QUESTIONS
- 12FEES AND INSURANCE COVERAGE
- 13BOOK AN APPOINTMENT
UNDERSTANDING PRESBYOPIA
What is presbyopia? How does vision change after 40?
Accommodation: the eye’s ability to focus
To understand presbyopia, you first need to understand accommodation. Accommodation is the eye’s natural ability to increase its optical power to focus the image, by deliberately creating myopia in itself. It is this mechanism that allows you to switch from distance vision to near vision, a bit like a camera’s autofocus.
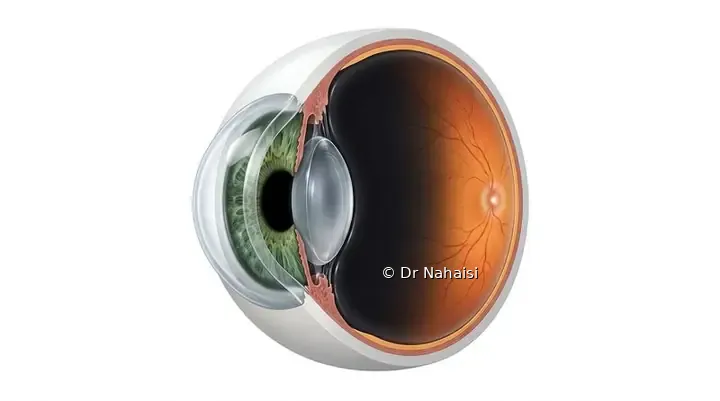
This mechanism relies on thecrystalline lens, the natural lens located inside the eye, just behind the iris. The crystalline lens is surrounded by a ring-shaped muscle, theciliary muscle. When this muscle contracts, it changes the shape of the crystalline lens. It makes it bulge, which increases its optical power and allows you to see clearly up close.
A teenager has an accommodation reserve of about10 to 12 diopters. That is enormous. It is what allows them to switch instantly from distance vision to reading a text a few centimeters away.
Presbyopia: a gradual decline, not an on/off switch
Presbyopia does not work like an on/off switch. It is a gradual decline of this accommodation reserve. With age, the crystalline lens loses its flexibility and the ciliary muscle loses contractility. The reserve decreases year after year:
- Aroundage 25: still about 8 diopters of reserve. No discomfort. The eye switches from distance to near effortlessly.
- Aroundage 40–42: about 3 to 4 diopters. The first symptoms appear. You hold your phone farther away, look for light to read small print, and tire more quickly when reading.
- Aroundage 50: about 1 to 2 diopters. The discomfort becomes clear-cut. Reading without glasses is difficult, screen work is tiring, and in farsighted people distance vision also starts to decline.
- Aroundage 55–60: almost zero accommodation reserve. The presbyopia has stabilized.
It is a universal and inevitable phenomenon. Everyone becomes presbyopic, without exception, whether nearsighted, farsighted, astigmatic or emmetropic. How it shows up, however, differs depending on the underlying refractive error.
Presbyopia progresses throughout life, but its symptoms start to appear around age 40–45 and increase until 60. Operating on presbyopia at 45 means operating on a phenomenon that will continue to progress. Operating at 55 means operating on a phenomenon that has almost stabilized.
For near vision, the young eye focuses thanks to accommodation: the flexible crystalline lens bulges and brings the image back onto the retina. With age, the crystalline lens stiffens and can no longer bulge. Up close, the image then forms behind the retina and becomes blurry. This is presbyopia, and it is why you hold your phone farther away to read.
How it shows up: different depending on your profile
The mechanism of presbyopia is the same for everyone. How it shows up, however, depends entirely on your initial vision problem.
For emmetropic people (no refractive error): near vision gradually declines. You hold your phone farther away, look for light, and small print becomes blurry. Distance vision remains perfect. These patients generally start with simple reading glasses, worn occasionally for reading and screens, and then sometimes switch a few years later to progressive lenses as the addition increases.
For farsighted people: presbyopia adds to an existing problem. Farsighted people used their accommodation to compensate for their refractive error, including for distance vision.When this reserve decreases, it is first the large accommodation efforts that become impossible: near vision drops first, around age 40. Then even small accommodation efforts are lost, and distance vision deteriorates in turn, around age 50. Presbyopic farsighted people then end up with a double problem, often discovered late in those with mild hyperopia, who did not necessarily wear glasses before. This translates into reading glasses in the first years, then permanent wear of progressive lenses once distance vision starts to decline.
For nearsighted people: it is the opposite situation, and often the most favorable. Nearsighted people still see blurry at distance as before, but they naturally keep good near vision when they take off their glasses, because their myopia acts as a “built-in zoom” for near vision. That is why people often say that nearsighted people “will always see up close.” The higher the myopia, the closer the natural reading point. Presbyopic nearsighted people often keep their old glasses for the first few years, taking them off when needed for near vision. Fairly quickly, they feel the need to switch to progressive lenses to avoid constantly putting them on and taking them off.
Progressive lenses and the addition: understanding your prescription
Progressive lenses are the most common optical solution for presbyopia. A single lens combines several zones of different power. The upper part of the lens corrects distance vision, the lower part corrects near vision, and a transition zone between the two provides intermediate vision (screen, dashboard). That is why you learn to lower your gaze to read and raise your head to look into the distance.
On your prescription, the ophthalmologist notes anaddition (written “Add”) once presbyopia appears. This addition corresponds to the extra power, on the lower part of the lens, needed for near vision to compensate for what your crystalline lens no longer does. An addition of +1.50 means that the reading zone of your lenses is 1.50 diopters stronger than the distance zone.
This addition increases by about +0.50 every 3 to 5 years, until it stabilizes at around +2.50 to +3.00 at age 55–60.
Can presbyopia be cured?
No. The crystalline lens cannot be given back its former flexibility. Many compensations are possible, however, to regain everyday visual comfort and considerably reduce visual discomfort.
The principle of these compensations always remains the same, whether progressive glasses, multifocal contact lenses or laser surgery: artificially creating what the crystalline lens no longer does naturally.
CORRECTION STRATEGIES DEPENDING ON YOUR PROFILE
How is presbyopia treated with a laser depending on whether you are nearsighted, farsighted or emmetropic?
There is no standard treatment for presbyopia. The strategy depends entirely on your initial profile, your needs and your visual habits.
The concept of the dominant eye
Before talking strategy, you need to understandocular dominance. Just as you are right-handed or left-handed, you have a dominant eye and a non-dominant eye. The dominant eye is the one the brain favors for distance vision and precision. The non-dominant eye tolerates slight distance blur better. It is always determined during the pre-operative assessment, and it shapes the choice of strategy.
Nearsighted and presbyopic: blended vision
Presbyopic nearsighted people are in a particular, often favorable, situation. It all comes down to one idea:to see up close without having to accommodate, you need to be nearsighted. A nearsighted eye is naturally set for near vision. Without glasses, a nearsighted person sees blurry at distance and well up close. That is why presbyopic nearsighted people take off their glasses to read: their uncorrected myopia serves as their near vision.
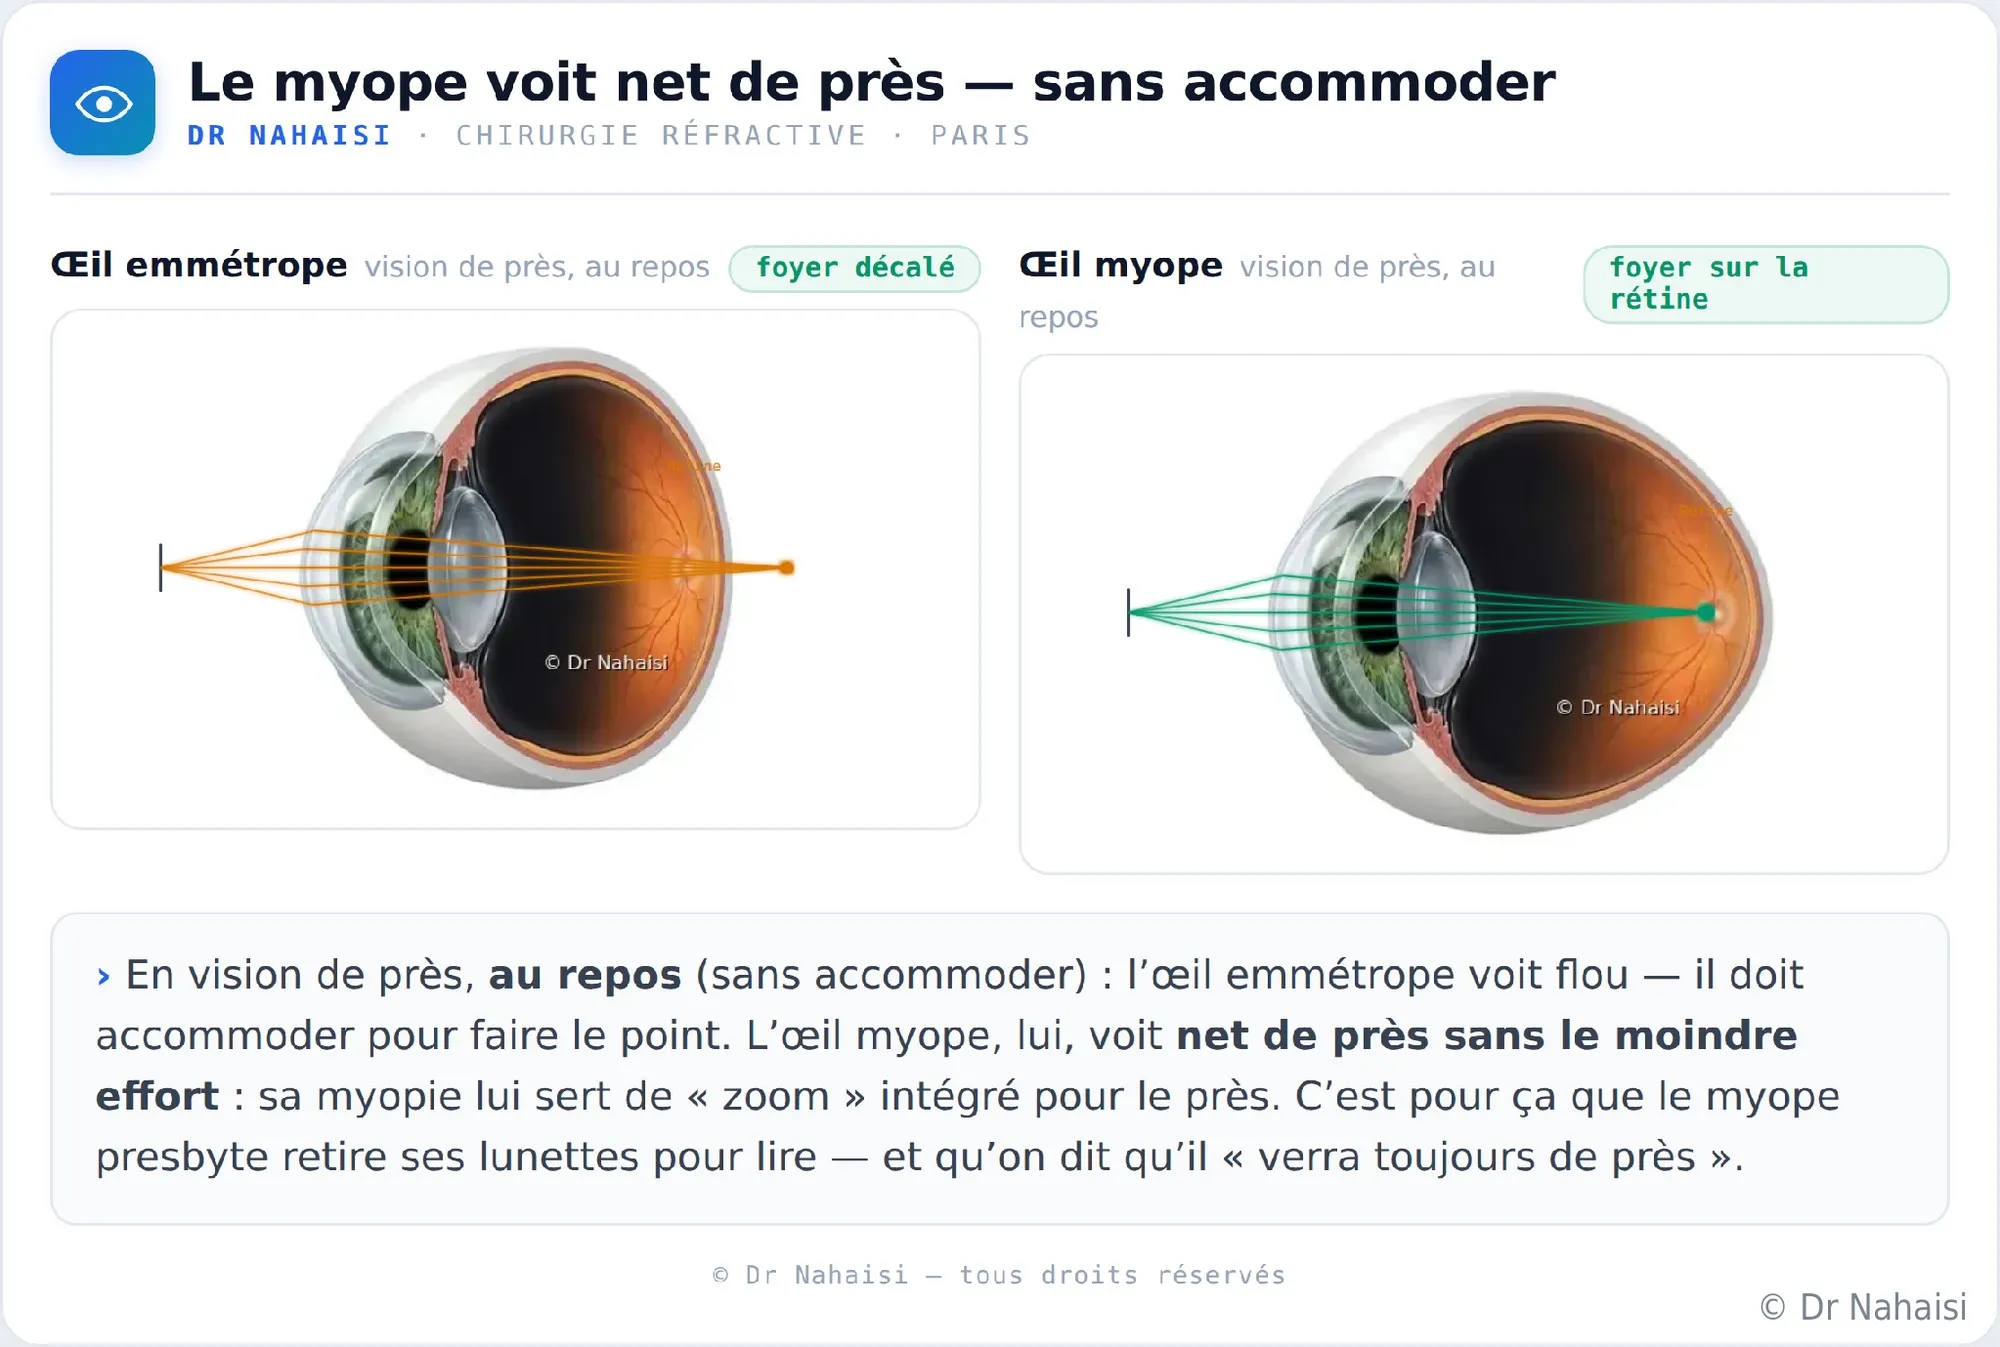
For near vision, at rest, the emmetropic eye sees blurry: it has to accommodate to focus. The nearsighted eye, on the other hand, sees clearly without the slightest effort, its myopia serving as built-in near vision. Blended vision relies on this. A little myopia is deliberately left in the non-dominant eye to preserve this natural near vision.
The strategy for presbyopic nearsighted people is in fact myopia surgery, with a differential correction. All the myopia is removed in the dominant eye, for distance vision, and about-1.50 diopters is deliberately left in the non-dominant eye, to preserve near vision. This is what is calledblended vision (monovision): one eye sees at distance, the other sees up close.
It is a standard LASIK. Each eye receives a simple monofocal treatment, with a different target. There is no multifocal profile here, unlike the PresbyMAX treatment used for emmetropic and farsighted patients. The brain learns to use the eye that sees best depending on the distance. It sorts things out on its own, and patients adapt to it very well.
We always test this blended vision with contact lenses before surgery so that the patient can experience the effect. If the trial works, it is a very good sign. Often, depending on the initial myopia, operating on just one eye may be enough to achieve the right balance.
What if you prefer to correct everything? That is entirely possible. Some nearsighted patients prefer to correct all the myopia in both eyes and then wear reading glasses. The important thing is to find the balance that suits YOU. It will change your life either way.
Emmetropic and presbyopic: multifocal presbyLASIK
Presbyopic emmetropic people have always had perfect vision, at distance as well as up close, and discover glasses for the first time around age 42–45. This is often the most frustrated profile.
In emmetropic people, there is no existing refractive error to work with: there is no myopia to keep. Blended vision for nearsighted people, with one nearsighted eye and the other emmetropic, therefore cannot be transposed. The laser will createmultifocality directly on the cornea, by sculpting a multifocal profile with thePresbyMAX module of the Schwind laser. This is what is calledpresbyLASIK.
Corneal multifocality works like this: the laser sculpts zones of different power on the cornea. Acentral zone, slightly myopic, dedicated to reading. Anemmetropic peripheral zone, dedicated to distance vision. This amounts to dividing the eye’s total optical capacity and distributing it across different viewing distances.
The compromise here is very clear. You start from perfect distance vision and accept reducing it very slightly to gain near vision. The treatment can be performed on just one eye, the non-dominant eye, to minimize the impact on distance vision, or on both eyes depending on the chosen strategy and the patient’s needs.
Farsighted and presbyopic: real relief
Multifocal laser surgery can feel like a real relief for farsighted patients. For them, presbyopia only worsens a problem that was already there.
Farsighted people used their accommodation to compensate for their distance refractive error. When presbyopia sets in, this reserve decreases and the problems add up: around age 40, near vision drops first; around age 50, distance vision deteriorates in turn. Presbyopic farsighted people end up struggling up closeand at distance.
The laser will steepen the cornea with a multifocal profile, which corrects hyperopia and compensates for presbyopia in the same step. It is a double benefit, and farsighted patients are often among the most satisfied after surgery.
THE TECHNIQUES: BLENDED VISION, PRESBYMAX AND PRESBYLASIK
How does laser presbyopia correction actually work?
There are two main approaches, depending on the patient’s profile.
Blended vision (nearsighted patients): standard LASIK with a differential
For nearsighted patients, we use standard monofocal LASIK, with no multifocal profile. We simply program a different target for each eye: full correction in the dominant eye for distance vision, partial correction in the non-dominant eye, which keeps a little myopia for near vision.
Why no multifocality for nearsighted patients? Because they do not adapt well to multifocal profiles. Simple blended vision works better, it can be tested with contact lenses beforehand, and the results are very good.
PresbyLASIK with PresbyMAX (emmetropic and farsighted patients)
For emmetropic and farsighted patients, we use thePresbyMAX module of theSchwind Amaris 750S laser. This software calculates a multifocal ablation profile. It sculpts the cornea so that it distributes light rays across several focal points: one for distance vision, one for intermediate vision, one for near vision.
PresbyMAX offers three treatment modes:
PresbyMAX monovision profile. The dominant eye receives amonofocal treatment for distance vision. The non-dominant eye receives a multifocal profile with one focal point for intermediate vision and one for near vision. This is the ideal profile when the patient needs to keep excellent distance vision: tennis player, golfer, frequent driver, outdoor work, hiker, sailor.
PresbyMAX hybrid profile. Both eyes receive a multifocal treatment, but with a different distribution. The dominant eye is mainly oriented toward distance vision (about 80%), with some intermediate vision. The non-dominant eye, as in monovision, is oriented toward intermediate and near vision. The resulting compromise is gentler than pure monovision: the difference between the two eyes is less marked, the transition between distance and near more natural, and intermediate vision on a computer screen is often better. This is the profile I favor for patients who work a lot on screens, read regularly, or have a near-vision-oriented lifestyle.
PresbyMAX micromonovision profile. This third mode is the most oriented toward near vision: the dominant eye is set mainly for intermediate vision, with only 20–30% of focus for distance vision. It penalizes distance vision too much for most patients, and I almost never use it. It could be useful in very specific cases, for example a seamstress who would like to be able to sew very close up for hours without glasses. This scenario remains rare.
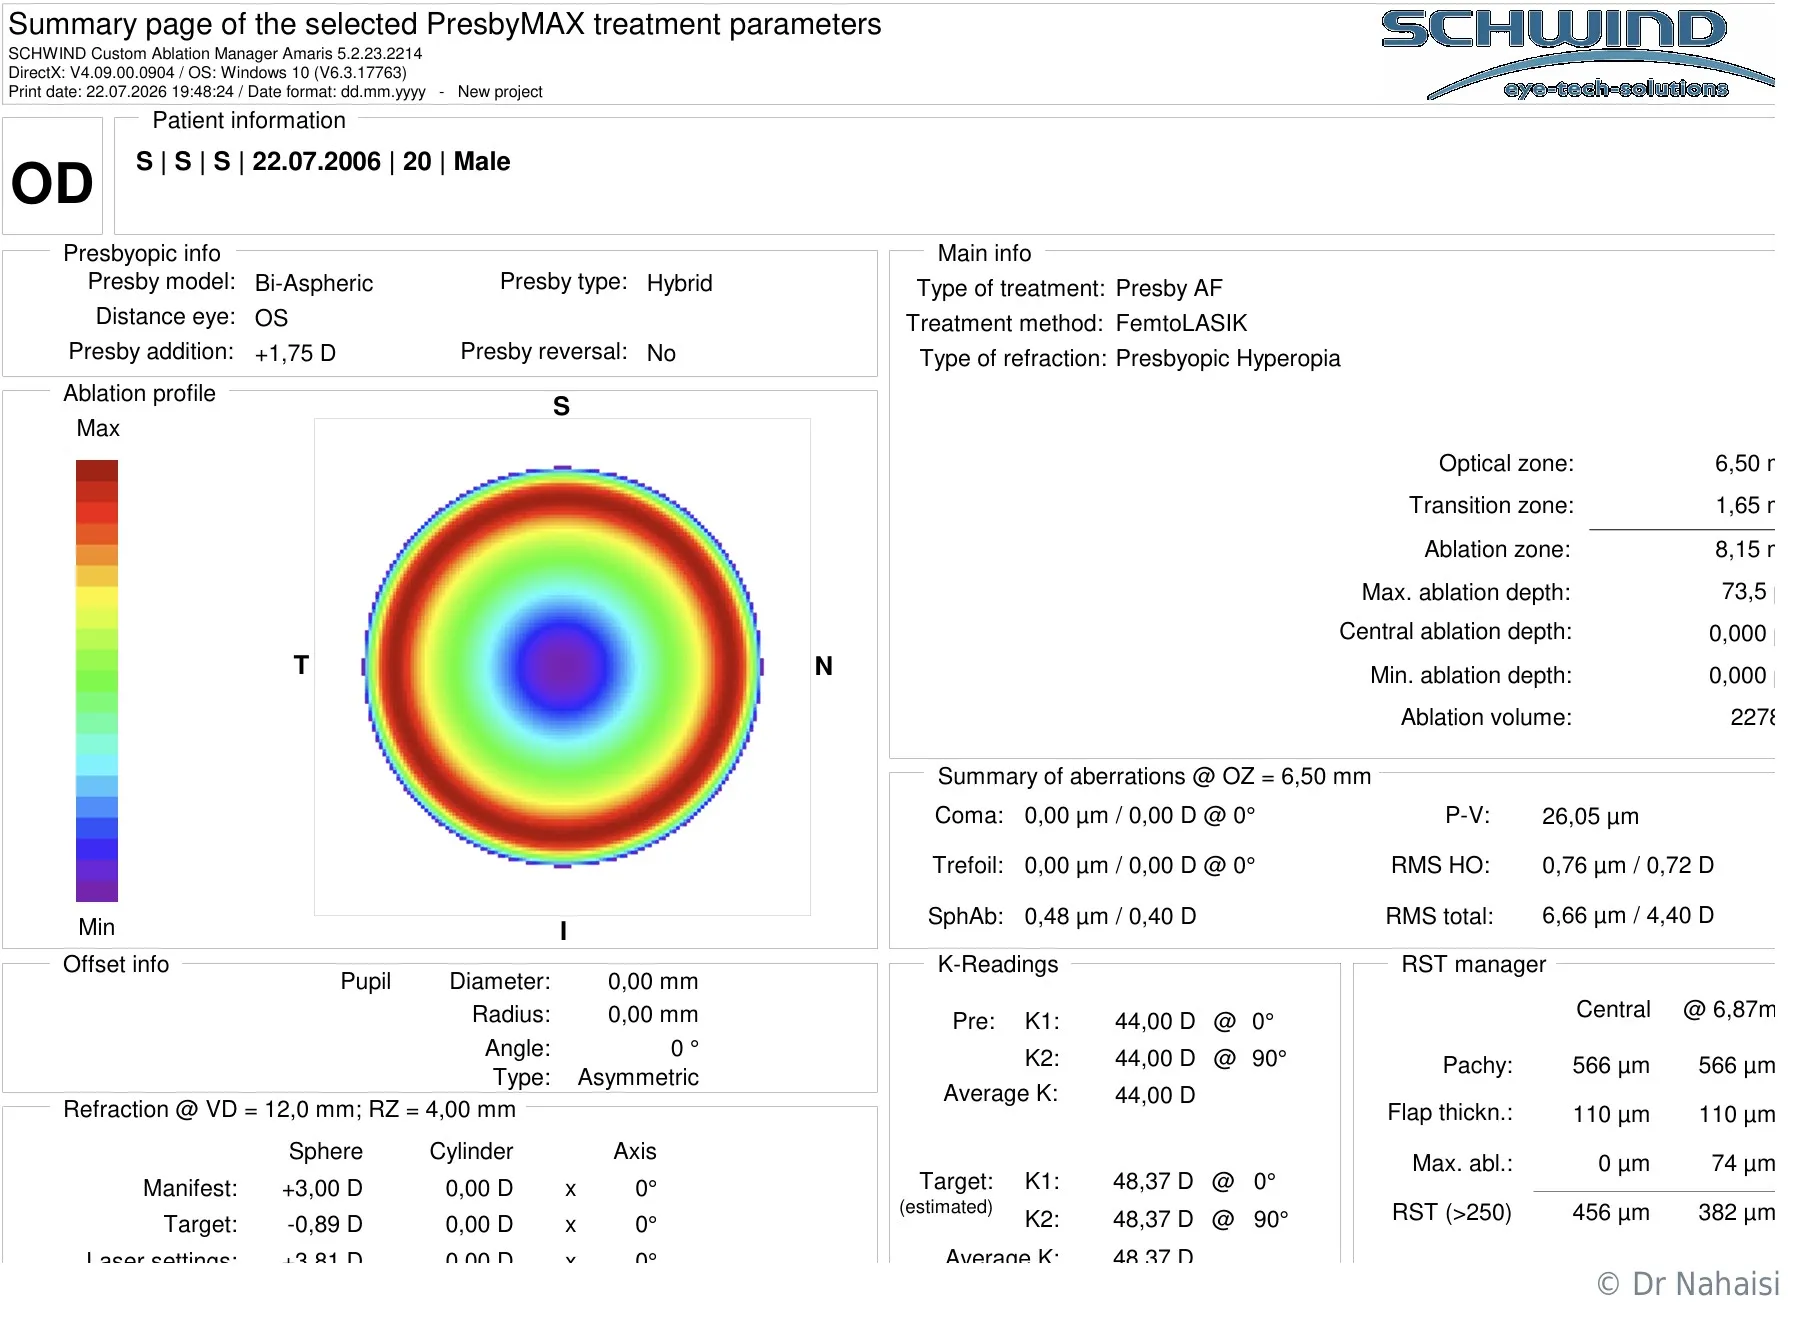
Here is the treatment planPRESBYMAXfor a farsighted patient with +3.00 diopters, who is also presbyopic.The laser removes tissue in the periphery, on the red ring, and spares the center, which ends up relatively steeper. It is on this type of cornea that the PresbyMAX module adds multifocality, by modulating the sculpting between the center and the periphery to provide both distance and near vision.
How do we choose between blended vision and presbyLASIK?
The choice follows directly from the profile:
Nearsighted patients → blended vision (standard LASIK with a myopic differential). Tested with contact lenses beforehand. No multifocality.
Emmetropic and farsighted patients → presbyLASIK with PresbyMAX. The choice between monovision and hybrid is made during the consultation, based on your needs. Someone who needs very good distance vision (sports, driving, outdoor work) will rather be steered toward the monovision profile. Someone who works on screens, reads a lot or has a near-vision-oriented lifestyle will rather be steered toward the hybrid profile.
The final decision is made case by case, in discussion with the patient, taking into account the initial prescription, visual habits and the data from the pre-operative tests.
Presbyopia and astigmatism: a simultaneous correction
Most presbyopic patients also have associated astigmatism, even if mild. The laser corrects both components during the same procedure, whether with blended vision for nearsighted patients with astigmatism or with PresbyMAX presbyLASIK for emmetropic or farsighted patients with astigmatism. The ablation profile automatically incorporates the astigmatism correction into the presbyopia correction.
THE DISTANCE/NEAR COMPROMISE AND HALOS
What is the distance/near compromise and what visual effects should you know about?
The compromise: trading dependence on glasses for a balance
Every presbyopia treatment relies on a compromise: distance vision quality is slightly reduced to regain near vision. You do not get back the eyesight you had at 20. The goal is toeliminate dependence on glasses in about90% of everyday activities.
You go from permanent dependence on glasses, progressive or reading glasses, sometimes several pairs, to almost complete freedom. You see fairly well at distance, fairly well up close. It is not 100% everywhere. That is the price of the compromise.
In most cases, this small loss in distance vision is imperceptible in everyday life. Some patients still keep a backup pair of glasses, on the nightstand for reading in the evening, or in the glove compartment for long drives. They can help from time to time, but you can perfectly well live without them.
Halos: a common and temporary effect
Halos are a typical effect of multifocal presbyopia treatments. They appear mainly at night, when the pupil is more dilated: point light sources, such as headlights or streetlights, are surrounded by a halo or a light streak.
They result directly from multifocality. The cornea now distributes the rays across several focal points, and when the pupil dilates in the dark, these different focal points create stray images around light sources.
These halos are more pronounced during the first month or two, then gradually fade. The peak is generally around the second month, after which they decrease steadily. The brain learns to filter them out, and most patients no longer notice them after a few months.
For the rare patients who do not adapt to halos, the reversibility of the treatment on the Schwind PresbyMAX platform makes it possible to reduce or cancel the multifocal effect.
TRANSPRK FOR PRESBYOPIA
Can presbyopia be treated with TransPRK rather than LASIK?
Yes. Both techniques use the sameSchwind Amaris 750S excimer laser and the same PresbyMAX ablation profiles. The difference lies in how the cornea is accessed.
PresbyLASIK creates a corneal flap that is lifted, with a painless procedure and very fast recovery. TransPRK is an “all-laser, no-contact” technique: the laser directly removes the epithelium and then sculpts the desired profile, with no flap.
TransPRK is less comfortable in the first few days, with 48 hours of discomfort, stinging and watery eyes, and visual recovery takes7 to 10 days. On the other hand, it barely weakens the corneal architecture. It is therefore preferred for patients whose cornea is a little thin or slightly irregular.
BEFORE SURGERY
How do you prepare for laser presbyopia surgery?
The consultation and pre-operative assessment
No prescription from your ophthalmologist is needed; you can come directly. The assessment is a complete exam: visual acuity, refraction, aberrometry, corneal topography, eye pressure, fundus exam, determination of the dominant eye. All of this is entered into the laser’s calculation software to determine the most suitable ablation profile.
The consultation is at the standard rate set by French national health insurance. At the offices in Paris 10th and 19th (10e and 19e arrondissements), there is no fee supplement and nothing to pay upfront (direct billing). At the Institut Voltaire (Paris 11th, 11e arrondissement), you pay €50 upfront, including a €30 fee supplement. Your complementary health insurance reimburses at least €20, and often the full amount depending on your plan.
Discover the patient journey from A to Z
The contact lens trial: mainly for nearsighted patients
The contact lens trial is mainly useful fornearsighted patients, to test blended vision before committing. We fit a pair that reproduces the differential planned for surgery: one eye sees at distance, the other keeps a little myopia for near vision. The patient can live with them for a few days or a few weeks and experience the effect.
If the trial works, it is a very good sign. If it is not quite right, we adjust the parameters and do further trials until we find the right balance. I remain available by message throughout the trial period to gather your impressions and adjust the combination. Generally, two or three trials are enough, and thanks to my experience I find the right combination on the first try in more than 80% of cases.
If blended vision still does not suit you despite the adjustments, there is no obligation. You can then opt for a full correction of the myopia with reading glasses as a complement.
For emmetropic and farsighted patients, a multifocal contact lens trial is not really representative of the surgical result with PresbyMAX. The strategy is instead decided during the consultation, based on the tests and the discussion.
THE SURGERY AND RECOVERY
How does laser presbyopia surgery work and what is recovery like?
How the procedure goes
The procedure is done on an outpatient basis at the Institut Voltaire, on Wednesday afternoons or Friday mornings. It takes about ten minutes in total for both eyes.
For presbyLASIK: the femtosecond laser (Visumax 800) creates the flap in a few seconds, the surgeon lifts it, then the excimer laser (Schwind Amaris 750S) sculpts the PresbyMAX profile in about twenty seconds. The flap is put back in about thirty seconds and adheres immediately.
For TransPRK: the laser does everything in a single pass, removing the epithelium and sculpting the cornea, without any contact with the eye. About one minute of laser per eye.
Surgery day: a detailed walkthrough of the procedure
Recovery after presbyLASIK
The first few hours: a gritty feeling in the eyes, sensitivity to light, watery eyes. Sunglasses are provided. A good nap is usually enough.
What is specific to presbyLASIK: in the first few days, near vision is often quite good, but it isdistance vision that may be bothersome. This is normal and temporary; the distance/near balance gradually settles over about a month. You should not judge the result in the first few days.
Resuming activities: screen work and driving are possible from the next day in the vast majority of cases. Post-operative eye drops for about a month. Check-up on the Monday afternoon following the surgery.
Recovery after TransPRK
First 48 hours: marked discomfort, with stinging, watery eyes and sensitivity to light. Visual recovery is gradual. Allow7 to 10 days before regaining good functional vision, and several weeks for the stabilized result. Time off work may be necessary.
RESULTS AND REALISTIC EXPECTATIONS
What should you expect after laser presbyopia surgery?
The goal is independence from glasses for distance and near vision in about90% of situations in everyday life: reading your phone, working on a screen, driving, watching TV, shopping, cooking.
Prolonged reading of very small print, subtitles at the movies, or reading in dim light in the evening may remain somewhat limited. For these situations, a small backup pair of glasses may be enough, on the nightstand or in the glove compartment, for example.
Post-operative visual fluctuations
It is normal to have fluctuations in vision, especially in the first month. Vision can vary over the course of the day: better in the morning, a little less sharp at the end of the day. Dry eye, common after surgery, plays a role in these fluctuations. The brain also needs time to adapt.
Vision in low light is always a little worse than in full light. These are normal variations.
Stability of the treatment over time
The laser treatment islong-lasting. Corneal remodeling can sometimes slightly reduce its effectiveness over several years, but this regression is not systematic. You may very well keep the same result for life.
If slight regression does occur, you never go back to what you had before surgery anyway. And if the patient is operated on before presbyopia has fully stabilized, before age 55–60, an enhancement may be considered a few years later.
REVERSIBILITY AND ENHANCEMENTS
Is laser presbyopia treatment reversible?
Yes, this is one of the great advantages of theSchwind PresbyMAX platform. The corneal flap created during the initial procedure can be lifted again, even months or years later. A reverse laser treatment is then performed to give the cornea back its former curvature, which reduces or cancels the multifocal effect.
This reversal is very rarely performed. It concerns patients who do not adapt to multifocality, who are too bothered at distance or by halos. If the compromise does not suit you, there are always options.
The role of the Schwind platform in reversibility
TheSchwind platform keeps all the data from the initial treatment and makes it possible to calculate a reverse treatment adapted to each eye. The laser “knows” exactly what it did and can precisely program the profile needed to adjust or cancel the treatment. At the Institut Voltaire, we are fortunate to have this equipment for our patients. With the right platform, it is entirely feasible.
Enhancement: timing and conditions
We wait at least 6 months after the initial surgery to allow the cornea to heal and the result to stabilize. If an enhancement turns out to be necessary, it is generally quick and simple: lifting the existing flap and a new laser pass.The enhancement is included in the first year. After that, a preferential rate applies up to 5 years after surgery.
Complex cases and custom treatments
For complex cases, such as decentrations, post-operative irregular astigmatism, or retreatments after previous surgery, we work in direct collaboration withJonathan Fimbel, the Schwind application engineer in France. He calculates custom ablation profiles in “ocular wavefront” or “corneal wavefront” mode, based on the patient’s aberrometry and topography.
FEES AND INSURANCE COVERAGE
How much does laser presbyopia treatment cost in Paris?
The fee depends on the strategy used:
Blended vision (presbyopic nearsighted patients): €3,200 for both eyes. This is the fee for standard LASIK with a myopic differential, with no multifocal profile.
PresbyLASIK (presbyopic emmetropic and farsighted patients): €1,800 per eye, or €3,600 for both eyes, whatever the chosen profile (PresbyMAX monovision or hybrid). The extra cost compared with standard LASIK is due to the cost of the multifocal profile calculated by the Schwind laser.
The exact quote is specified during the consultation, based on the strategy defined together.
These fees cover the surgery, unlimited post-operative follow-up, and any enhancement in the first year. After that, a preferential rate applies up to 5 years after surgery.
Payment is made on the day of surgery, by bank card, check or bank transfer. It can also be spreadover 4 installments, by check or direct debit.
Refractive surgery is not reimbursed by French national health insurance, but many complementary health insurance plans cover part of the costs. I provide a personalized quote for you to send to your insurer.
Learn more about fees, quotes and complementary health insurance reimbursement
Frequently asked questions
Your questions about laser presbyopia surgery
Up to what age can you have laser presbyopia surgery?
Laser presbyopia surgery (presbyLASIK or TransPRK) can be performed up to age 60, or even 65, as long as the eyes are suitable. Age is not an absolute contraindication. What matters are the characteristics of the eye: thickness and regularity of the cornea, clarity of the crystalline lens, condition of the retina. After age 55–60, if an early cataract isdetected, laser treatment will not be the best option and lens surgery with an implant will need to be considered.
Is laser presbyopia surgery painful?
No. The eye is numbed with drops before the procedure. During surgery, there may be some discomfort or a brief feeling of pressure, but no pain. After the procedure, you will feel a gritty sensation in the eyes, watery eyes and sensitivity to light for a few hours. By the evening or the next day, most patients resume their usual activities.
Are halos common after laser presbyopia surgery?
Yes, halos are a common and expected effect after any multifocal presbyopia treatment. They are linked to the distribution of rays across several focal points on the cornea. They appear mainly at night, around headlights and streetlights. They are more pronounced during the first month or two, then gradually fade. The brain learns to filter them out. In the very rare cases where they remain bothersome, the treatment can be reversed on the Schwind PresbyMAX platform we use at the Institut Voltaire.
I am nearsighted and presbyopic. Can only the myopia be corrected without treating the presbyopia?
This is a request I receive very often from presbyopic nearsighted patients: “I already see well up close without my glasses, I just want to improve my distance vision.” Beware of the trap. If all the myopia is corrected identically in both eyes, both eyes become perfectly sharp at distance, but at the same time the natural near vision the myopia provided is lost. You will then need reading glasses, like any non-nearsighted person over 45. That is why we usually suggest blended vision instead, which preserves near vision in the non-dominant eye. That said, if you really prefer to correct only the myopia in both eyes and then wear reading glasses, that is entirely possible. The important thing is to find the balance that suits YOU. We discuss it together during the consultation, and you will have all the information you need to decide.
After laser presbyopia surgery, is it normal to see differently from one eye to the other?
Yes, and that is actually how surgical correction of presbyopia works, whether it is blended vision (one eye for distance, the other for near) or multifocal presbyLASIK (different profiles in each eye). Above all, do not cover one eye to compare. Live normally with both eyes open. The brain sorts things out on its own and adapts within a few days to a few weeks.
Should both eyes be operated on at the same time in presbyopia surgery?
Not necessarily. Depending on your initial prescription and the chosen strategy (blended vision for nearsighted patients, presbyLASIK for emmetropic or farsighted patients), operating on just oneeye may be enough to achieve the desired balance. This is decided together during the consultation, based on your needs and your profile.
I have high eye pressure or glaucoma. Is laser presbyopia surgery possible?
Being treated for high eye pressure, especially in the absence of confirmed glaucoma, is not a problem for refractive surgery. Laser surgery has no effect on glaucoma; they are two separate problems. You will simply need to continue your usual monitoring after the procedure: eye pressure, visual fields, OCT. In the case of confirmed glaucoma, multifocal treatments should be avoided, but a monofocal treatment may still be considered, on a case-by-case basis.
I have strabismus. Is it compatible with laser presbyopia surgery?
The combination of convergent strabismus (esotropia) and hyperopia is common. If the strabismus improves with glasses correction, it means it is linked to the accommodative effort caused by the hyperopia. The laser corrects the hyperopia and thus reduces the trigger of the strabismus. Each case is discussed individually during the consultation.
How long does it take for the result of presbyLASIK to stabilize?
The functional result (everyday vision) settles quickly: a few days for presbyLASIK, a few weeks for TransPRK. The truly stabilized result is assessed after 3 to 6 months, once corneal healing is complete and the brain has adapted to the new distribution of light rays.
What if I am not happy with the result of my presbyopia surgery?
If after the stabilization period (6 months minimum) the result is not satisfactory, such as persistent distance discomfort, insufficient near vision, or poor tolerance of the compromise, we can operate again. Options range from a simple enhancement (adjusting the profile) to a complete reversal of the treatment (giving the cornea back its previous curvature). Reversibility is one of the great advantages of the Schwind PresbyMAX platform.
What are the risks of laser presbyopia surgery?
The most serious risk is post-operative infection, which is extremely rare and treatable with antibiotics. You do not lose an eye with this surgery. The result may sometimes fall short of expectations: under-correction, over-correction, asymmetric healing between the two eyes. An enhancement is then possible after stabilization. Dry eye is common in the first few weeks, but temporary. Halos are common with multifocal treatments, temporary, and reversible if they persist.
Can I drive soon after laser presbyopia surgery?
In general, driving is possible from the day after the procedure. Surgery days are on Friday mornings, the post-operative check-up is on Monday afternoon, and most patients drive again from the beginning of the following week.
I live far from Paris. How do I organize my laser presbyopia surgery?
We regularly see patients from elsewhere in France, from the French overseas territories (DOM-TOM) and from abroad. The typical arrangement: a first consultation with a pre-operative assessment in Paris, then the procedure scheduled a few days or a few weeks later. The post-operative check-up takes place on the Monday afternoon following the Friday surgery. Longer-term follow-up can be provided by an ophthalmologist near you.
Do I need a referral letter from an ophthalmologist to book a consultation for presbyopia surgery?
No. You do not need a referral letter or prescription from your ophthalmologist for a refractive surgery consultation. You can book an appointment directly on Doctolib or by phone.
I have an early cataract. Is laser presbyopia treatment still an option?
If the crystalline lens is still clear and the cornea healthy, the laser remains an excellent option for treating presbyopia. If, however, a significant early cataract is detected, corneal laser treatment will be less appropriate. Lens surgery with an implant will then need to be considered, during which presbyopia can also be treated. This procedure is performed by specialized colleagues.
I am nearsighted and had surgery when I was young. When will presbyopia set in?
Presbyopia will set in around age 42–45, whether or not you have had myopia surgery. It is a natural phenomenon linked to the aging of the crystalline lens, independent of refractive surgery. If your myopic correction remains stable until then, you will need reading glasses at that age anyway. A laser enhancement to treat presbyopia is then entirely possible.
BOOK AN APPOINTMENT
Ready to regain your visual freedom?
The first step is simple: a consultation to review your eyes, your prescription and the options available to you. No commitment, no pressure, just a full assessment and a frank discussion.
Book an appointment on Doctolib
Phone and WhatsApp:01 84 80 28 04 · Email:nahaisi@laservisionparis.com · Doctolib messaging
Download the information booklet (PDF)
Author: Dr Steven Nahaisi, ophthalmic surgeon specializing in laser refractive surgery, Institut Laser Ophtalmologique Voltaire (Voltaire Laser Eye Institute), Paris 11th.
Your surgeon
Dr Steven Nahaisi
Ophthalmic surgeon dedicated exclusively to laser refractive surgery. He operates at the Institut Laser Ophtalmologique Voltaire and consults in three Paris offices. Consultations in English.
